
Demodex that reaches the cornea: early, small-study evidence for adding IPL
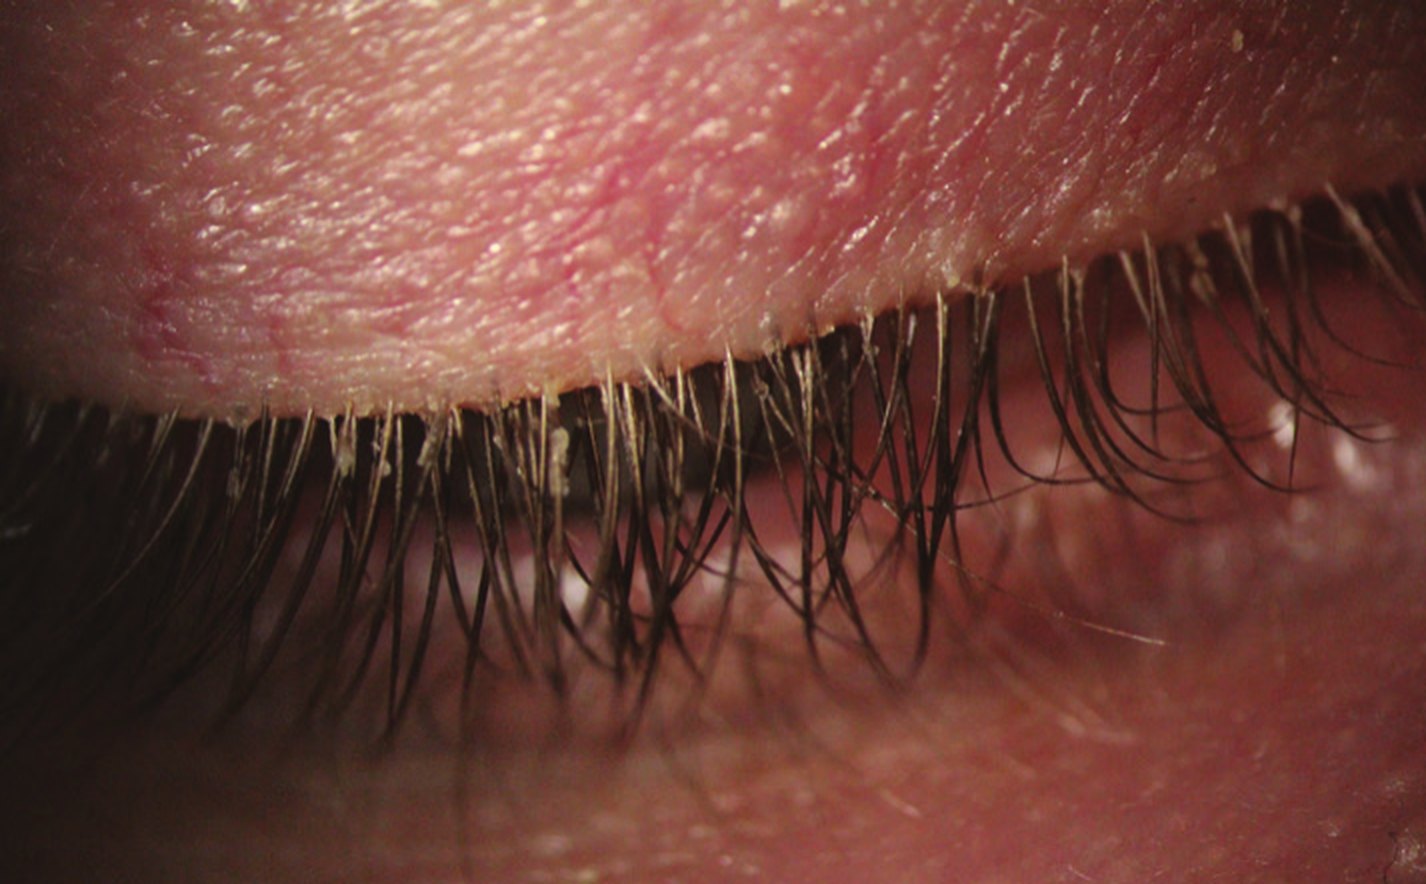
Most people with Demodex mites on their eyelashes have itchy, crusty, irritated lids and nothing more. In a smaller group the inflammation spreads from the lid margin to the cornea, the clear window at the front of the eye. Clinicians call this blepharokeratoconjunctivitis (BKC), and it can affect vision. A 2026 paper in Annals of Medicine looked at whether adding intense pulsed light (IPL) to standard treatment was associated with better results in these patients.
We read the full text. The short version: the results are interesting, but this is early, small-study evidence. It was retrospective, from a single hospital, not randomised, and only 10 patients had IPL. It cannot show that IPL caused the differences.
What the study did
Researchers at a corneal clinic in Hangzhou, China, went back through the records of 45 consecutive patients seen between January 2022 and January 2024. All had mites confirmed under the microscope, typical cylindrical dandruff on the lashes and corneal involvement. Ages ranged widely and included some children.
Thirty-five patients had conventional treatment and 10 had IPL added. Nobody was randomly assigned. The choice depended on how stubborn the disease had been, on patient preference after a discussion that included out-of-pocket cost, and on whether the device was available.
What "conventional treatment" meant
Both groups received the same medicines and lid hygiene:
- a steroid eye drop (0.1% fluorometholone or loteprednol) four times a day, reduced weekly and stopped after one month
- artificial tears four times a day
- tobramycin and dexamethasone ointment on the lid margin two to three times a day, then every other day after the first week
- ofloxacin ointment at bedtime
- tacrolimus drops twice a day for severe corneal inflammation
- 0.05% cyclosporine drops and artificial tears as maintenance after the first month
- tea tree oil based lid wipes twice a day in the first month and once a day in the second
- in-clinic lid margin cleaning with a motorised sponge brush when debris had built up
The conventional group also had meibomian gland heating and massage, started one to two weeks in, once the acute corneal inflammation had settled.
The IPL protocol
The IPL group had IPL in place of the heating and massage. The device was a Lumenis M22 with a small contact light guide. Energy started at 15 J/cm2 and was increased at each session, typically not exceeding 24 J/cm2. After anaesthetic drops, an eye shield and gel, the upper and lower eyelids were treated in turn. The paper does not report how many sessions each patient had or how far apart they were.
What it found
The median delay from first symptoms to diagnosis was 1.5 years, and 17 of 45 patients had first been given another diagnosis, most often viral keratitis. Patients with more mites tended to have worse corneas: each extra mite per three lashes was associated with 32% higher odds of the central cornea being involved (odds ratio 1.32, 95% CI 1.08 to 1.62). That is an unadjusted association, not proof of cause.
Then the between-group comparison:
- Corneal blood vessels. At a median of 3.2 months, new corneal vessels had resolved in 7 of 10 IPL patients (70.0%) and 9 of 35 conventional patients (25.7%), P = 0.004.
- Tear film stability. Tear break-up time improved by 3.5 ± 1.2 seconds with IPL and 1.7 ± 0.8 seconds without, P < 0.001.
- Vision. At six months, best-corrected acuity had improved by 0.19 ± 0.12 logMAR with IPL and 0.11 ± 0.09 without, P = 0.024.
- Recurrence. By six months, 1 of 10 IPL patients (10.0%) and 12 of 35 conventional patients (34.3%) had flared again, P = 0.236.
A P-value is the probability of seeing a difference this large if the treatments were really equal; below 0.05 is the usual threshold for "unlikely to be chance". A 95% confidence interval (CI) is the range within which the true value plausibly lies. On that basis the recurrence difference was not statistically significant, even though the abstract describes recurrence as reduced.
No IPL-related adverse events were recorded, and eye pressure was similar in both groups (13.8 versus 14.2 mmHg). Ten patients is too few to judge safety.
Signs, not just symptoms
All of the reported outcomes are clinical signs. The paper says IPL patients had more relief from itch and redness but gives no symptom scores. It also concludes that IPL reduced mite burden without reporting mite counts after treatment in the results. Those two claims could not be checked.
What the studies can't tell us
- The groups may differ. Allocation was by clinical judgement, preference and cost. At baseline, 80.0% of the IPL group had corneal vessels versus 48.6% of the conventional group. That gap was not statistically significant, but it muddies the comparison.
- Unmasked. No masking of the examiners is described, and several outcomes are judged by eye at the slit lamp.
- Small and exploratory. Several outcomes were tested in 45 patients with no primary outcome named, which the authors acknowledge raises the risk of chance findings.
- IPL replaced something. The comparison is IPL versus heating and massage on top of the same medicines, not IPL versus nothing.
- Internal inconsistencies. Some figures in the discussion do not match the results tables, and a few baseline numbers differ between text and table.
- Short follow-up. Six months, at one hospital, with one device.
- Funding. We could not find a funding or conflict of interest statement in the text we retrieved.
The authors call the findings hypothesis-generating and ask for randomised trials.
What this means for you in Hamilton
The more useful message may be about diagnosis, not IPL. Recurrent chalazia, lash dandruff and a red eye that keeps returning deserve a careful look at the lids and cornea. If Demodex is found, treatment starts with the lids; our earlier post on Demodex blepharitis and in-clinic lid cleaning covers that ground. Purpose-made lid cleansers, such as the tea tree oil based Blephadex eyelid foam cleanser, are available from the Rose Optometry online store; this is not the wipe used in the study, and home-mixed tea tree oil should never go near the eyes.
IPL has a larger evidence base for meibomian gland dysfunction, which we summarise in IPL for dry eye: the evidence and on our IPL therapy page. For Demodex that has reached the cornea, this study is a reason for further research, not a basis for promises. Corneal involvement needs prompt assessment and usually prescription medicines. The optometrist team at Rose Optometry in Hamilton can examine your lids and cornea and discuss which options are suitable for you. The optometrists at Rose Optometry are Anjali Hira, Emilie Lawson, Jacqueline Rowe, Jagrut Lallu, Jason Shen, Jessica Wood and Stella Wong, and dry eye care is part of their clinical practice.
Rose Optometry is part of the Dry Eye Specialist Group, alongside Visique Rototuna Optometrists and other member practices. If you live outside Hamilton, your local Dry Eye Specialist Group member practice is the place to start.
Reference
- Yang S, Wang N, Meng Q, Lin L, Wang L, Jin X. Clinical characteristics and preliminary retrospective evidence of adjunctive efficacy of intense pulsed light therapy for Demodex-associated blepharokeratoconjunctivitis: a single-center study. Annals of Medicine. 2026;58(1):2639675. PMID 41795646. https://doi.org/10.1080/07853890.2026.2639675
